


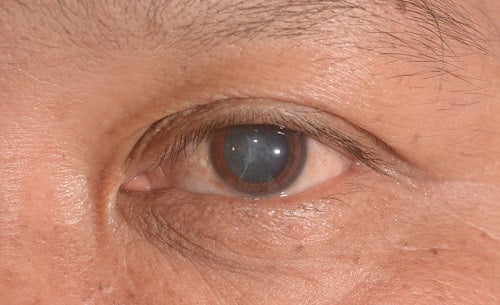
Cataracts are common, but diabetes changes the risk profile and care plan. Understanding cataracts and diabetes helps you prepare for appointments, surgery discussions, and long-term eye health. This guide explains mechanisms, compares cataract types, and outlines surgery considerations for people living with diabetes.
Key Takeaways
- Higher risk and earlier onset: Diabetes can accelerate lens clouding.
- Pre-op planning matters: Glycemic stability reduces surgical complications.
- Retina follow-up is essential: Monitor for macular edema and retinopathy.
- Prevention helps: Glucose control, UV protection, and regular exams support vision.
Understanding Cataracts and Diabetes
A cataract is a clouding of the eye’s natural lens that scatters light and blurs vision. In diabetes, long-term hyperglycemia (high blood sugar) speeds lens protein changes and water shifts. The result can be earlier cataract development and faster progression compared with people without diabetes. Risk varies with age, duration of diabetes, and comorbid eye disease.
People with diabetes also face a higher chance of coexisting conditions, such as diabetic retinopathy (retinal blood vessel disease) and macular edema (retinal swelling). These conditions can limit visual recovery after cataract surgery if not managed. Scheduling regular dilated exams allows the eye care team to coordinate timing, imaging, and treatments. For a concise primer on retina risks, see Diabetic Eye Disease for background on retinopathy stages and symptoms.
How Does Diabetes Cause Cataracts?
The lens has no blood supply and depends on surrounding fluids for nutrients. Elevated glucose diffuses into the lens and is converted to sorbitol via the polyol pathway (sugar-to-sorbitol pathway). Sorbitol accumulates, draws water into lens fibers, and disrupts transparency. Oxidative stress and nonenzymatic glycation (sugar attaching to proteins) further destabilize lens proteins and promote clouding.
These biochemical shifts can fluctuate with short-term glucose changes, sometimes causing transient focus changes. Over time, the structural damage becomes permanent lens opacity. Certain lens patterns are more frequent in diabetes, including anterior/posterior cortical changes and posterior subcapsular opacities. This metabolic pathway explains why patients with long-standing hyperglycemia often need surgery earlier. For an accessible reference, the NEI cataract overview offers general pathophysiology and symptoms without treatment directives.
Comparing Diabetic Cataract vs Age-Related Cataract
Age-related cataracts typically evolve slowly, with nuclear sclerosis (central yellowing/hardening) as a hallmark. In diabetes, posterior subcapsular changes may appear earlier and cause more glare and near-vision problems. Fluctuating sugar levels can add variable focusing, which feels like day-to-day prescription shifts. Patients may also notice quicker functional impact relative to the amount of visible lens opacity.
Overlapping patterns are common, especially in older adults with type 2 diabetes. Your clinician will grade the cataract, assess the macula, and review retinopathy status. The mix of cataract types influences lens choice, surgical approach, and postoperative medication plan. When planning education and screening, see Cataract Awareness Month for timely reminders about exams and symptom tracking.
Pre-Op Planning and Glycemic Stability
Patients often ask about the permissible sugar level for cataract surgery. There is no universally accepted single glucose or A1C cut-off; clinicians focus on stability, overall health, and infection risk. Acute metabolic issues, such as severe hyperglycemia or ketoacidosis, can prompt deferral until safe. Many teams coordinate with primary care to optimize blood pressure, lipids, and glucose before scheduling.
Preoperative imaging (OCT) evaluates for macular edema. If retinopathy is active, the retina specialist may suggest anti-VEGF therapy or laser before or around the time of surgery. For context on intravitreal options used in diabetic retinal disease, see Lucentis Prefilled Syringe as a medication profile reference used in retina care. Broader pre-op guidance is also outlined by major groups; the AAO guidance discusses glycemic considerations without strict thresholds.
Surgery Outcomes and Recovery in Diabetes
Patients sometimes wonder, do diabetics take longer to heal after cataract surgery. Most people recover well, but the presence of retinopathy or macular edema can slow visual improvement. Surgeons often tailor anti-inflammatory drops, sometimes adding nonsteroidal agents, to reduce swelling risk. Postoperative schedules may be more frequent to catch changes early.
Intraocular pressure (IOP) spikes can occur after surgery, especially with steroid drops. People with ocular hypertension or glaucoma risk may need closer monitoring. For a medication overview related to IOP control, see Timolol as a commonly referenced beta-blocker drop page. For systemic risk perspective across organs, the article Type 2 Diabetes Complications summarizes how long-term control supports safer recoveries.
Retinopathy and Postoperative Monitoring
The progression of diabetic retinopathy after cataract surgery is an important discussion. Evidence suggests surgery can transiently increase retinal inflammation, with short-term risk of macular edema in susceptible eyes. Care teams mitigate this with pre-op imaging, staged treatments, and targeted drop regimens. Scheduled dilated exams and OCT monitoring are key after the procedure.
If edema appears, clinicians may add topical NSAIDs, adjust steroids, or coordinate retina injections. Many patients still achieve meaningful gains, but expectations should align with baseline retinal health. For practical self-care habits that complement clinic follow-up, see Eye Health Amid Diabetes for everyday steps that support ocular stability. Broader diabetic eye risks are described by the NEI retinopathy page in patient-friendly terms.
Type 2 Diabetes and Cataract Surgery: Timing and Technique
Care plans for type 2 diabetes and cataract surgery emphasize coordination. The surgeon evaluates cataract density, pupil behavior, and any prior laser or injections. They may choose an incision, lens type, and drop protocol suited to inflammation risk. Monofocal lenses remain standard; premium lenses require careful macular assessment because subtle retinal changes can limit their benefit.
Some surgeons pre-treat or co-treat retinopathy to stabilize the macula before surgery. Others schedule early postoperative retina checks to detect edema. Discuss work demands, night driving, and glare to tailor lens power and target refraction. For topic navigation across eye care content, the category links Ophthalmology and Diabetes organize related articles and updates.
Prevention and Long-Term Habits
Daily choices influence cataract prevention in diabetes. Aim for stable glucose through diet, activity, and medications as directed by your clinician. Wear UV-blocking sunglasses to reduce ultraviolet exposure to the lens. Avoid smoking, which accelerates oxidative stress in the eye. Protective steps do not reverse existing cataracts, but they may slow progression.
Schedule routine dilated eye exams based on your provider’s plan. Report glare, halos, and contrast loss early, especially if driving at night. Nutritional balance supports overall ocular health; for context, see Vitamin E and Diabetes for a neutral overview of diet considerations. For calendar-based reminders and public health context, Healthy Vision Month offers timely checklists and preventive messages.
What to Expect at the Consultation
Your ophthalmologist will review vision goals, medical history, and current medications. They will perform biometry (lens power measurement), corneal topography (shape mapping), and dilated retinal exam. Optical coherence tomography (OCT) provides a detailed cross-section of the macula, which guides both lens selection and drop choices. Bring a medication list and recent A1C if available.
Discuss how glare affects driving, reading, and work tasks. Ask about lens options, postoperative restrictions, and return-to-activity timelines. Clarify how diabetes management fits with the surgical plan, including any adjustments around the day of surgery. For seasonal reminders and community resources, explore Diabetes Education Week for practical tools and education prompts.
Recap
Diabetes increases cataract risk and can complicate surgery planning, but most patients do well with coordinated care. Stabilizing glucose, checking the retina, and setting realistic goals improve outcomes. Use regular exams and simple habits to protect vision over time.
This content is for informational purposes only and is not a substitute for professional medical advice.











