



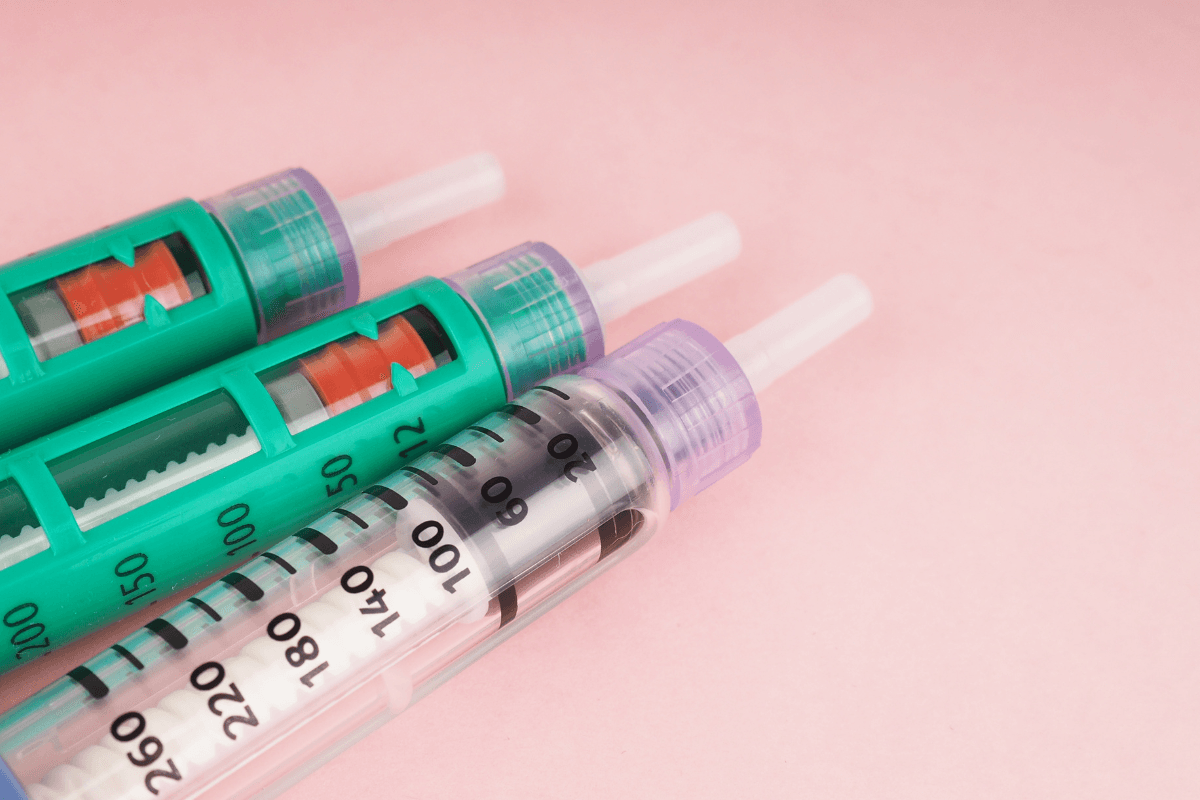
Choosing between byetta vs bydureon requires understanding how each exenatide formulation works in daily life. Both belong to the glucagon-like peptide-1 (GLP-1) receptor agonist class (incretin-mimicking hormone), yet they differ in dosing frequency, devices, and safety nuances. This guide summarizes practical points, then highlights availability and switching considerations. Use it to frame a balanced discussion with your healthcare team.
Key Takeaways
- Same Active Molecule: Both use exenatide, delivered differently over time.
- Dosing Rhythm: Byetta is twice daily; Bydureon is once weekly.
- Device Differences: Pens and autoinjectors change handling steps.
- Safety Nuances: GI effects, rare pancreatitis, and thyroid warnings.
- Access Factors: Market availability and supply can shift.
Byetta vs Bydureon: Core Similarities and Differences
Byetta (exenatide immediate-release) and Bydureon (exenatide extended-release) share the same active drug but deliver it on different schedules. Byetta provides short pulses before meals, which may blunt post-meal glucose rises. Bydureon releases exenatide slowly over a week, smoothing exposure and reducing dosing burden. These pharmacologic profiles can shape appetite effects, gastrointestinal tolerability, and convenience.
Both agents belong to the GLP-1 family, which helps enhance glucose-dependent insulin secretion and slow gastric emptying. For a concise class overview and mechanism details, see GLP-1 Receptor Agonists Drugs. If you need Byetta-specific background before comparing, review Byetta Uses Side Effects Dosage for indications and key precautions.
Dosing, Devices, and Injection Technique
Byetta is administered subcutaneously twice daily before the two main meals, while Bydureon is injected once weekly on the same day each week. Bydureon’s delivery has used different devices over time, including reconstitution pens and an autoinjector. The current device landscape matters because it influences preparation steps, needle handling, and training time for users and clinics.
Clarify which presentation your pharmacy supplies and review instructions specific to that device. Some patients may encounter the phrase bydureon bcise 2 mg autoinject on packaging or clinical notes. For step-by-step device differences and indications, see Bydureon Exenatide Uses Dosage And Side Effects for device-specific context. If you want needle size and compatibility details for ancillary supplies, see BD Ultrafine II Syringes as an example of common injection equipment.
Tip: Keep a simple injection log. Recording date, site rotation, and any local reactions can help clinicians troubleshoot technique and tolerability.
Efficacy and Weight Effects in Type 2 Diabetes
Both formulations help reduce hemoglobin A1c as part of a comprehensive plan that includes nutrition, physical activity, and other therapies when appropriate. Some individuals also notice appetite suppression and modest weight change. Weight effects vary by person and by formulation exposure over time. Weekly agents may produce steadier gastrointestinal effects but can still cause early nausea during titration.
Clinical interest often centers on bydureon weight loss because weekly dosing can simplify adherence while supporting calorie awareness. Real-world results vary with diet quality, activity levels, and concomitant medications. For further context on patient-reported outcomes and study summaries, see Bydureon Weight Loss for weight-related considerations and counseling points.
Safety Profile and Adverse Effects
Common effects include nausea, vomiting, diarrhea, and decreased appetite. These typically lessen over time but can recur after dose changes. Rare but serious events include pancreatitis; seek urgent care for severe, persistent abdominal pain that may radiate to the back. Patients with significant gastrointestinal disease or reduced gastric motility should review risks before starting a GLP-1 agent.
Bydureon BCise carries a boxed warning about thyroid C-cell tumors observed in rodents; its relevance to humans is unknown. Byetta does not carry this boxed warning. Both products have detailed contraindications and precautions in their labels. For adverse effect patterns and monitoring checklists, see Bydureon Side Effects for structured safety discussions. For formal label language on risks and warnings, refer to the FDA prescribing information for Bydureon BCise and the FDA labeling for Byetta.
Patients and clinicians also search for bydureon bcise side effects when troubleshooting persistent nausea or injection-site nodules. Care teams may adjust timing, counsel on smaller meals, or consider antiemetic strategies when appropriate. Always review renal function, prior pancreatitis, and any thyroid neoplasm history before selection.
Availability, Discontinuations, and Alternatives
Availability of exenatide products can vary by country, wholesaler, and time. Market updates sometimes include supply constraints, packaging changes, or formal withdrawals. Pharmacies may substitute presentations depending on stock and regional approvals. If a device presentation changes, clinicians should re-educate patients on mixing steps and needle disposal to maintain safe technique.
Recent marketplace updates have prompted searches such as bydureon bcise discontinued and product replacement options. Status may differ across jurisdictions and over time. For the latest market situation, check manufacturer communications, national formularies, or drug shortage lists. The ADA Standards of Care provide neutral therapy positioning when specific products face supply issues. For curated alternatives across weekly GLP-1 options, see Ozempic vs Bydureon to understand how semaglutide compares when exenatide is unavailable.
Note: Availability can change quickly and may be region-specific. Confirm current stock and approved presentations with your pharmacy and insurer before making a switch.
Switching and Conversions Between GLP-1 Agents
When medication access, side effects, or goals change, switching within the GLP-1 class may be considered. Practical transitions focus on minimizing overlap, watching for gastrointestinal effects, and avoiding gaps that could destabilize glucose control. Individualized plans consider A1c trends, fasting versus post-meal patterns, renal function, and concomitant agents such as SGLT2 inhibitors or DPP-4 inhibitors.
Clinicians sometimes reference bydureon to trulicity conversion when planning a weekly-to-weekly change. Generally, teams align dosing days, monitor nausea, and reassess targets two to four weeks after stabilization. For side-by-side context on another weekly agent, see Trulicity vs Bydureon to compare device steps and titration schemes. If you prefer a detailed comparison across multiple injectables, see Injectable Type 2 Diabetes Medications List for classifications and examples.
Principles to Guide Safe Switching
Switching should aim to maintain glucose stability without duplicating active drug exposure. Start by clarifying the last dose date, then plan the next agent’s initiation at a logical interval, balancing washout with sustained coverage. Counsel patients to expect short-term GI symptoms, eat smaller meals, and hydrate to reduce nausea. Revisit background therapies, especially sulfonylureas or insulin, to reduce hypoglycemia risk when appetite changes. Schedule early follow-up for symptom review and self-monitoring data. For patients with kidney disease, apply extra caution and consider agents with renal outcome data.
Clinical Scenarios and Patient Selection
Twice-daily Byetta may suit patients who want mealtime flexibility or who need targeted post-prandial control. Weekly Bydureon can support those prioritizing convenience, steady exposure, and fewer injections. Needle phobia, dexterity limitations, and mixing steps can tip preferences toward simpler devices. Educators should match device complexity to a patient’s comfort and support network.
Some teams consider switching from bydureon to ozempic when seeking stronger A1c reduction potential or once-weekly pens with different titration paths. Others reconsider exenatide after persistent nausea or nodules and explore alternatives. For broader therapy mapping across mechanisms, see Diabetes Medications List for where GLP-1, SGLT2, and DPP-4 agents fit, and Dapagliflozin for a representative SGLT2 option that may complement GLP-1 therapy.
Compare With Other GLP-1 Options
Newer incretin-based therapies broaden choices across weekly and daily schedules. Efficacy, tolerability, and device familiarity often drive selection when coverage is similar. Consultation with diabetes educators can help tailor a plan that aligns with lifestyle and monitoring capacity. As products evolve, formulary status and device updates can also shift preferences.
Questions sometimes include bydureon vs mounjaro when comparing exenatide with dual GIP/GLP-1 agonists. Head-to-head data, if available, guide interpretation, but mechanism differences and titration speed also matter. For structured comparisons within the exenatide family, see Bydureon vs Victoza for a daily versus weekly lens, and Ozempic vs Bydureon for semaglutide-specific context. For weight-focused indications, review Zepbound to understand a tirzepatide option used for chronic weight management.
Recap
Both exenatide options can support glucose control, but their dosing rhythms and devices feel different in daily life. Match the formulation to patient priorities, teach the device carefully, and monitor tolerability and glucose patterns. When availability changes, plan transitions deliberately to maintain continuity and safety. Revisit goals regularly as lifestyle, preferences, and coverage evolve.
For additional background across GLP-1 choices and related therapies, see Type 2 Diabetes for educational articles and Diabetes Products to understand categories and device types.
This content is for informational purposes only and is not a substitute for professional medical advice.











