


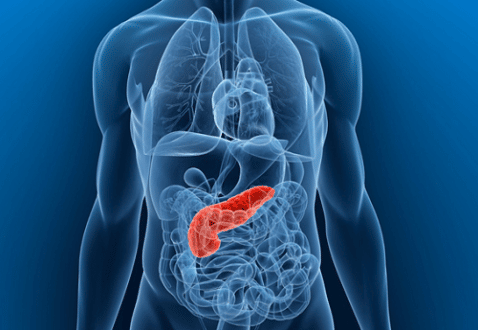
Understanding how the pancreas and blood sugar regulation interact helps prevent complications. This guide connects clinical facts with practical steps you can discuss with your healthcare team.
Key Takeaways
- Two-way relationship exists between pancreatic inflammation and glucose control.
- High triglycerides and gallstones are common pancreatitis triggers.
- Type 3c (pancreatogenic) diabetes can follow pancreatic damage.
- Nutrition, alcohol limits, and monitoring help stabilize glycemia.
The term pancreatitis and diabetes describes a bidirectional link that influences diagnosis and care. Clear definitions, careful monitoring, and coordinated follow-up reduce avoidable risk.
Pancreatitis and Diabetes: Understanding the Link
The pancreas has exocrine functions (digestive enzymes) and endocrine functions (insulin and glucagon). Inflammation can disrupt both systems, causing malabsorption and unstable glucose levels. Recurrent inflammation or scarring may reduce beta-cell capacity and blunt glucagon responses. This combination makes hypoglycemia more likely and glycemic targets harder to maintain.
In the opposite direction, insulin resistance, obesity, and severe hypertriglyceridemia can raise pancreatitis risk. Gallstones remain a leading cause, and alcohol use contributes in many settings. For diagnostic criteria and complication profiles, see the NIDDK pancreatitis overview, which outlines acute and chronic forms and their evaluation. For broader gastrointestinal context on pancreatic disease, explore our Gastrointestinal articles, which group related digestive topics for easier review.
Can Diabetes Cause Pancreatitis? Mechanisms and Risks
Multiple pathways may connect dysglycemia with pancreatic inflammation. Severe hypertriglyceridemia, often seen with insulin resistance, is a well-established cause of acute pancreatitis. When triglycerides exceed critical thresholds, toxic free fatty acids can injure acinar cells and capillaries. A detailed summary is available in this StatPearls review, which describes mechanisms and risk modifiers. Weight, gallstone disease, and alcohol also shape risk profiles.
Medication effects can be complex and are best individualized with clinicians. Some diabetes and weight medicines influence gastric emptying, appetite, or lipid profiles. For a cardiometabolic perspective on incretin-based therapy, see our Heart Benefits Overview, which discusses mechanisms beyond glycemic control. In insulin-resistant states, pancreatitis and diabetes type 2 can intersect with dyslipidemia; addressing triglycerides with diet, activity, and appropriate therapy may reduce events. Discuss lipid management options with your clinician; as background, Fenofibrate is one therapy used to treat high triglycerides.
Can Pancreatitis Lead to Diabetes? Type 3c Explained
Pancreatic inflammation or surgery can damage islet cells and the surrounding tissue, reducing insulin and glucagon secretion. This pattern often aligns with type 3c diabetes, sometimes called pancreatogenic diabetes. Patients may experience brittle glycemia due to combined endocrine and exocrine dysfunction. Malabsorption can cause erratic post-meal glucose, while impaired glucagon defenses raise hypoglycemia risk.
Diagnostic workup usually considers a history of pancreatitis, imaging evidence of pancreatic disease, and signs of exocrine insufficiency. C-peptide, autoantibodies, and fecal elastase testing may help differentiate from autoimmune or typical type 2 pathways. A deeper background is provided by this pancreatogenic diabetes review, which discusses features and clinical considerations. For structured fundamentals on classification and targets, see the ADA Standards of Care compilation, which clinicians reference to guide management decisions. For therapy context on GLP‑1 dosing principles, our Dosing Guide outlines practical use patterns that may inform discussions with your care team.
Symptoms, Red Flags, and When to Seek Care
Acute pancreatitis usually presents with sudden upper abdominal pain that may radiate to the back. Nausea, vomiting, fever, and rapid pulse are common. Severe cases can involve dehydration, low oxygen levels, and organ stress. Chronic forms may cause persistent discomfort, weight loss, steatorrhea (fatty stools), and disturbed glucose patterns. Unrelenting pain, vomiting, or signs of infection warrant urgent evaluation.
People often ask about pancreatitis when to worry. Concerning signs include severe or persistent abdominal pain, inability to keep liquids down, jaundice, confusion, and shortness of breath. Known gallstones, heavy alcohol use, and very high triglycerides increase risk. If you use GLP‑1 or similar therapies and develop concerning abdominal symptoms, contact your clinician promptly. For context on gastrointestinal effects with GLP‑1 medicines, see our neutral GLP-1 Comparison, which summarizes class similarities and differences.
Blood Sugar Patterns, Nutrition, and Alcohol
Glycemic patterns after pancreatic injury can be erratic, especially around meals. Exocrine insufficiency impairs digestion, which can flatten or delay glucose rises. Reduced glucagon can make insulin-induced lows harder to correct. Meal timing, macronutrient balance, and enzyme replacement (when prescribed) all influence day-to-day stability. Alcohol may worsen hypoglycemia risk and aggravate pancreatic inflammation.
Nutrition and Monitoring Priorities
Work with clinicians and a dietitian on individualized targets. Consistent carbohydrates, adequate protein, and attention to fat quality help stabilize postprandial responses. Pancreatic enzyme therapy, when used, should be coordinated with meals to improve absorption and reduce steatorrhea. Continuous or frequent glucose checks help capture delayed peaks and nocturnal lows. Weight management and gentle physical activity further support insulin sensitivity without overtaxing recovery.
For weight and appetite mechanisms relevant to GLP‑1 medicines, our Weight-Loss Drugs explainer outlines how these agents affect satiety and intake. If discussing medicine options that slow gastric emptying, reviewing device format and titration can help; see Victoza Pens for device features you might encounter in practice. Strategies should balance symptom control, nutrition needs, and safety. To support meal planning discussions, pancreatitis and diabetes diet considerations include smaller meals, lower alcohol intake, and attention to triglycerides.
Tip: If you drink alcohol, discuss safe limits with your clinician. Avoid binge patterns that can trigger inflammation and destabilize glucose.
Treatment and Long-Term Outlook
Care focuses on the underlying cause, symptom control, and tailored glycemic management. In acute episodes, fluids, pain control, and treating triggers (e.g., gallstones, very high triglycerides) are core priorities. Chronic care may include lipid optimization, nutrition therapy, pancreatic enzymes, and diabetes medications. Hypoglycemia education is important because glucagon responses may be blunted after pancreatic damage.
Team-based follow-up helps align endocrinology, gastroenterology, and nutrition goals. Your clinician may adjust medicines as symptoms evolve, especially after hospitalizations. For emerging oral incretin approaches and how they compare, see our Oral Incretins overview for mechanism and practical considerations. Discuss any therapy changes with your care team. In patients with overlapping needs, pancreatitis diabetes treatment plans consider enzymes, lipid therapy, and thoughtful glucose-lowering choices.
Prognosis and Follow-Up
Outcomes vary with the cause, severity, and recurrence of pancreatitis. Preventing new attacks, addressing gallstones, moderating alcohol, and reducing triglycerides can lower complications. Glucose control may remain challenging due to variable absorption and hormone responses. Regular monitoring for vitamin deficiencies, weight change, and bone health is useful when exocrine insufficiency is present.
Risk stratification improves with time. Type 3c diabetes life expectancy depends on overall cardiovascular risk, nutritional status, and success preventing recurrent inflammation. Practical goals include steady meal patterns, tailored activity, and avoidance of pancreatitis triggers. For long-term weight stability after therapy changes, our guide on Prevent Weight Regain offers behavior strategies that complement clinical care. Keep scheduled visits and update your team after any hospital care or medication changes.
Recap
The pancreas supports digestion and glucose control, so inflammation disrupts both systems. Diabetes can contribute to pancreatitis via lipids and metabolic stress, while pancreatic damage can produce pancreatogenic diabetes. Coordinated care, nutrition planning, and careful monitoring reduce avoidable risks and improve day-to-day stability.
This content is for informational purposes only and is not a substitute for professional medical advice.











